

Strabismus Surgery
Eye muscle surgery to improve eye alignment, treat double vision, or support binocular vision when non-surgical options are insufficient.
Strabismus surgery adjusts the muscles that control eye position to improve alignment. It is used when prism glasses are insufficient or impractical, and when the eye deviation is stable enough for surgical planning. The procedure is commonly performed in both children and adults, with technique chosen according to the measured pattern of misalignment.
Key takeaways
- Adjusts eye muscle position to improve alignment
- Treats double vision (diplopia), visible eye turns, or both
- Outpatient surgery with same-day discharge
- Multiple techniques are available, including adjustable sutures in selected adults
- Alignment and double-vision relief are different outcomes; improvement in one does not guarantee the other
- May require more than one surgery in some cases
If you are considering eye-muscle surgery, an adult strabismus surgery consultation can review stability, goals, and expected recovery.
How Strabismus Surgery Works
Mechanism
The eye is moved by six extraocular muscles, each controlled by a different nerve:
- Medial rectus: Turns eye inward (cranial nerve III)
- Lateral rectus: Turns eye outward (cranial nerve VI)
- Superior rectus: Turns eye up (cranial nerve III)
- Inferior rectus: Turns eye down (cranial nerve III)
- Superior oblique: Turns eye down and inward (cranial nerve IV)
- Inferior oblique: Turns eye up and outward (cranial nerve III)
Surgery changes how strongly the muscles pull by:
- Weakening overacting muscles (recession, myectomy)
- Strengthening underacting muscles (resection, plication)
- Repositioning muscles (transposition procedures)
When Surgery Is Considered
Indications
Double vision from:
- Sixth nerve palsy (stable for 6+ months)
- Fourth nerve palsy (stable)
- Third nerve palsy (stable, selected cases)
- Thyroid eye disease (stable phase)
- Post-traumatic strabismus
Childhood strabismus:
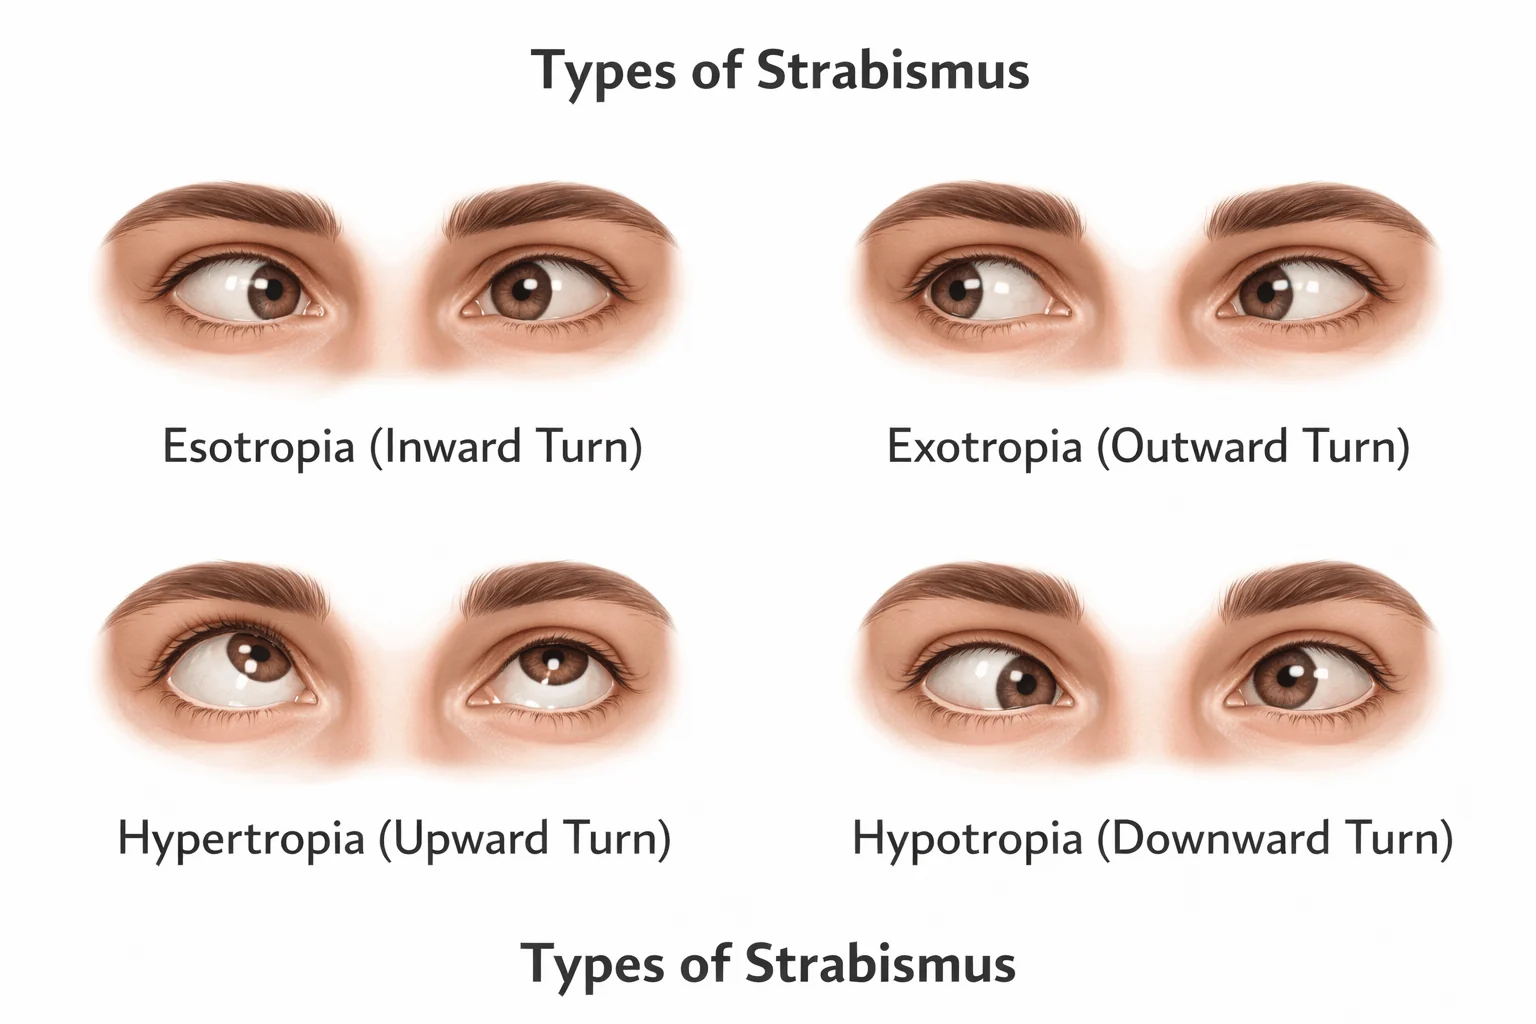
- Esotropia (eyes turn in)
- Exotropia (eyes turn out)
- To restore binocular vision and prevent amblyopia
Adult strabismus:
- Long-standing misalignment
- Nystagmus (Kestenbaum procedure to move null point)
- Functional and cosmetic concerns
Prerequisites
- Stable deviation: Not actively changing (typically wait 6+ months after cranial nerve palsy onset)
- Prisms not adequate: Too large for glasses, or cosmetically unacceptable
- Significant functional impact: Affecting daily activities, work, driving
- Or cosmetic concern: Even without double vision
When Surgery Is NOT Recommended
- Actively changing deviation (still recovering)
- Unstable myasthenia gravis (medical treatment first)
- Very recent onset (wait to see if spontaneous recovery occurs)
- Deviation well-controlled with prisms that patient tolerates
Types of Procedures
Recession
Weakening procedure: moves muscle insertion backward
- Most common technique
- Muscle detached from eye and reattached farther back
- Reduces the muscle's pulling effect
- Amount of recession (in mm) depends on deviation size
- The planned change depends on the measurements; the final alignment can vary
Resection
Strengthening procedure: shortens the muscle
- A portion of muscle is removed
- Remaining muscle reattached at original insertion
- Increases muscle's pulling power
- Often combined with recession of the antagonist muscle
Plication
Alternative strengthening procedure
- Muscle folded rather than cut
- May be reversible early after surgery
- Less commonly used
Adjustable Sutures
Allows post-operative fine-tuning
- A movable knot lets the surgeon change the muscle position shortly after surgery
- The patient usually needs to cooperate with alignment measurements
- The adjustment is often performed while awake with numbing eye drops; this is separate from the anesthesia used for the operation
- May be considered for reoperations, thyroid eye disease, or other complex deviations
The 2018 Cochrane review by Hassan and colleagues found only one small randomized study, involving 60 children followed for six months. Its low-certainty evidence did not establish which technique produced better alignment.
The broader 2022 AAO assessment by Heidary and colleagues found that most included nonrandomized studies favored adjustable sutures for alignment, but the findings were not uniform and high-quality randomized evidence was lacking. Adjustable sutures offer a way to refine alignment; they do not guarantee a better result for every patient.
Transposition Procedures
For complete muscle paralysis
- Muscles moved to new locations
- Helps when one muscle completely non-functional
- Examples: Knapp procedure, Hummelsheim procedure
- Used for complete sixth nerve palsy or third nerve palsy
Patient Selection
Evaluation Before Surgery
- Complete neuro-ophthalmic examination
- Measurements at multiple visits to confirm stability
- Prism and cover testing at distance and near
- Assessment in multiple gaze positions
- Forced duction testing (to check for restrictions)
- MRI if underlying cause unclear
Best Candidates
- Stable deviation for at least 6 months
- Clear surgical goal (eliminate diplopia, improve alignment)
- Realistic expectations
- Able to comply with post-operative care
- Underlying condition addressed (thyroid controlled, etc.)
What to Expect
Before Surgery
Pre-operative:
- Stop blood thinners if medically safe (discuss with prescribing doctor)
- Arrange transportation (no driving day of surgery)
- Nothing to eat or drink after midnight
- Continue eye drops and essential medications
Day of surgery:
- Arrive at surgical center as directed
- Pre-operative assessment and consent
- Anesthesia discussion
- Mark surgical site
During Surgery
Anesthesia:
- General anesthesia: most common, especially for children
- Local with sedation: an option for selected adults; adjustable sutures do not require this type of anesthesia
- Topical with sedation-selected cases
The procedure:
- Surgery performed on the white part of the eye (sclera)
- No incision through the cornea or into the eye
- Conjunctiva (clear membrane) opened to access muscles
- Muscles repositioned as planned
- Sutures close the conjunctiva
- Duration: 30-60 minutes per eye
After Surgery
Immediately:
- Recovery room monitoring
- Same-day discharge typical
- Eye may be patched briefly
- Mild pain, managed with acetaminophen or ibuprofen
First days:
- Red, sore eyes (normal, resolves over 1-2 weeks)
- Swelling of eyelids
- Some discharge
- Antibiotic and steroid drops as prescribed
- Avoid swimming, heavy lifting, dusty environments
First weeks:
- Gradually improving comfort
- Redness fading
- No driving until cleared by surgeon
- Return to work typically 1-2 weeks (office work sooner)
- Avoid contact sports for 2-4 weeks
Alignment during follow-up:
- Eye position can change during healing and later
- Your surgeon checks alignment and double vision across follow-up visits rather than promising a final result by a fixed week
- Adjustable-suture adjustments are made early after surgery when indicated; timing depends on the technique and surgeon's plan
Adjustable Suture Adjustment
If you have adjustable sutures:
- Return same day or next morning (depending on protocol)
- Topical anesthetic applied
- Surgeon tests alignment
- Sutures tightened or loosened as needed
- Brief discomfort during adjustment
- Allows early fine-tuning but does not guarantee the final alignment or relief of double vision
Risks and Complications
Expected Recovery Symptoms
- Redness: normal, resolves over weeks
- Soreness: controlled with over-the-counter pain relievers
- Swelling: temporary
Alignment and Vision Problems
- Over- or under-correction: some misalignment may remain or recur
- Persistent or new double vision: may require prisms or further surgery and may not fully resolve
AAPOS adult strabismus guidance identifies residual misalignment and persistent double vision among the most common surgical risks.
Less Common
- Infection: rare, treated with antibiotics
- Scarring: can affect eye movement
- Bleeding: usually minor, resolves
- Conjunctival cyst: may need treatment
Rare
- Scleral perforation: uncommon, can be repaired
- Retinal detachment: very rare
- Vision loss: extremely rare
- Anesthesia complications: standard risks apply
Outcomes and Success Rates
Defining Success
- Alignment: how closely the eyes line up at distance, near, and in different directions of gaze
- Visual function: whether double vision, head posture, or use of both eyes improves
- Patient goals: changes in comfort, daily activities, and appearance
These outcomes should be assessed separately. Better alignment does not guarantee relief of double vision, and a satisfactory early result can change over time.
The AAO review by Mills and colleagues found that adult strabismus surgery can improve alignment and visual function, based largely on observational case series. The studies involved different causes of strabismus and reported different results. A single success percentage cannot describe every adult or child, and published results are not Hashemi Eye Care outcome rates.
Factors Affecting Outcomes
Your surgeon considers the cause and pattern of misalignment, previous operations, whether measurements are stable, and your ability to use both eyes together. Thyroid-related restriction, prior surgery, and complex patterns can affect planning and the likelihood of further treatment. The technique is selected for your circumstances; it does not remove these uncertainties.
Need for Additional Surgery
Some patients need further surgery for residual or recurrent misalignment. Other operations are planned in stages. An early adjustable-suture adjustment is different from a repeat operation.
For a defined example, Oke and colleagues' 2022 IRIS Registry study followed 34,872 adults who underwent strabismus surgery in participating practices from 2013 through 2018. The overall reoperation rate within one year was 7.7%. That measures another operation during one year, not perfect alignment, relief of double vision, or the lifetime likelihood of another operation. The observational study does not establish an individual patient's risk or an HEC-specific rate.
If symptoms remain, follow-up measurements help determine whether prisms, more observation, or another operation is appropriate. There is no fixed number of operations that guarantees the desired result.
Comparison to Non-Surgical Treatments
| Treatment | Advantages | Disadvantages |
|---|---|---|
| Prism glasses | Non-invasive, reversible | Limited to smaller deviations, cosmetic concerns |
| Botox injection | Office procedure, temporary | Wears off, less predictable |
| Surgery | Can improve alignment and address large deviations | Surgical risks, recovery time, possible residual or recurrent misalignment |
For convergence insufficiency, the 2020 review by Scheiman and colleagues compares nonsurgical treatments such as exercises and prism glasses. It does not estimate success rates for strabismus surgery.
When Prisms Are Preferred
- Small, stable deviations
- Elderly or poor surgical candidates
- Patient preference
- Temporary deviations expected to resolve
When Botox May Be Used
- Temporary correction
- Diagnostic (to predict surgical outcome)
- Patients who cannot undergo surgery
- Acute sixth nerve palsy (controversial)
Living After Strabismus Surgery
Recovery Timeline
| Time | What to Expect |
|---|---|
| Day 1 | Sore, red, swollen eyes |
| Week 1 | Improving comfort, still red |
| Week 2 | Can usually return to work/school |
| Week 4 | Redness mostly resolved |
| Follow-up visits | Alignment and double vision are reassessed as healing progresses |
| Later follow-up | Check for residual or recurrent misalignment when symptoms or measurements change |
Long-Term
- Alignment and daily visual function may improve, but the degree of benefit varies
- Eye position can drift over time and double vision may persist or recur
- Prisms or additional surgery may be discussed if symptoms remain
- Continue follow-up with your ophthalmologist as recommended
Frequently Asked Questions
Will I be awake during surgery?
Most adults have the option of being asleep (general anesthesia) or having local anesthesia with sedation. Children typically have general anesthesia.
Is strabismus surgery painful?
You'll have anesthesia during surgery, so you won't feel pain. Afterward, eyes are sore for several days but this is manageable with over-the-counter pain relievers.
How long does recovery take?
Return to work and daily activities depends on the procedure, your symptoms, and your surgeon's advice. Redness can last weeks or occasionally months. Eye position is assessed during follow-up and can change over time; a fixed recovery date does not guarantee final alignment. Follow your surgeon's restrictions on driving, swimming, and heavy activity.
Will I need glasses after surgery?
Surgery corrects alignment but doesn't change your need for glasses. If you wore glasses before, you'll likely still need them. However, you may no longer need prisms.
What if the surgery doesn't work?
Your surgeon will reassess the eye position and any double vision, then discuss options such as prisms or further surgery. Additional treatment may help, but perfect alignment and single vision cannot be guaranteed.
Can strabismus surgery be reversed?
Surgery is generally considered permanent. However, if over-corrected, additional surgery can be done to improve alignment.
How many times can strabismus surgery be performed?
There is no set number that is right for everyone. Previous operations and scarring affect which options remain and how another procedure is planned. Your surgeon will explain whether further surgery is likely to help and what limitations to expect.
Will my insurance cover strabismus surgery?
Strabismus surgery is generally covered by insurance when performed for functional reasons (diplopia, abnormal head position). Coverage for purely cosmetic concerns varies.
References
- American Association for Pediatric Ophthalmology and Strabismus. Strabismus Surgery.
- American Association for Pediatric Ophthalmology and Strabismus. Adult Strabismus (Adult Eye Misalignment).
- American Association for Pediatric Ophthalmology and Strabismus. Adjustable Sutures in Strabismus Surgery.
- Mills MD, Coats DK, Donahue SP, Wheeler DT. Strabismus surgery for adults: a report by the American Academy of Ophthalmology. Ophthalmology. 2004;111(6):1255-1262. doi:10.1016/j.ophtha.2004.03.013.
- Hassan S, Haridas A, Sundaram V. Adjustable versus non-adjustable sutures for strabismus. Cochrane Database Syst Rev. 2018;3:CD004240. doi:10.1002/14651858.CD004240.pub4.
- Heidary G, et al. Adjustable Sutures in the Treatment of Strabismus: A Report by the American Academy of Ophthalmology. Ophthalmology. 2022;129(1):100-109. doi:10.1016/j.ophtha.2021.07.026.
- Oke I, et al. Adjustable Suture Technique Is Associated with Fewer Strabismus Reoperations in the Intelligent Research in Sight Registry. Ophthalmology. 2022;129(9):1028-1033. doi:10.1016/j.ophtha.2022.04.021.
- Scheiman M, Kulp MT, Cotter SA, Lawrenson JG, Wang L, Li T. Interventions for convergence insufficiency: a network meta-analysis. Cochrane Database Syst Rev. 2020;12:CD006768. doi:10.1002/14651858.CD006768.pub3. This review addresses nonsurgical convergence-insufficiency treatment.
Medical Disclaimer: This information is for educational purposes only and does not replace professional medical advice, diagnosis, or treatment.