

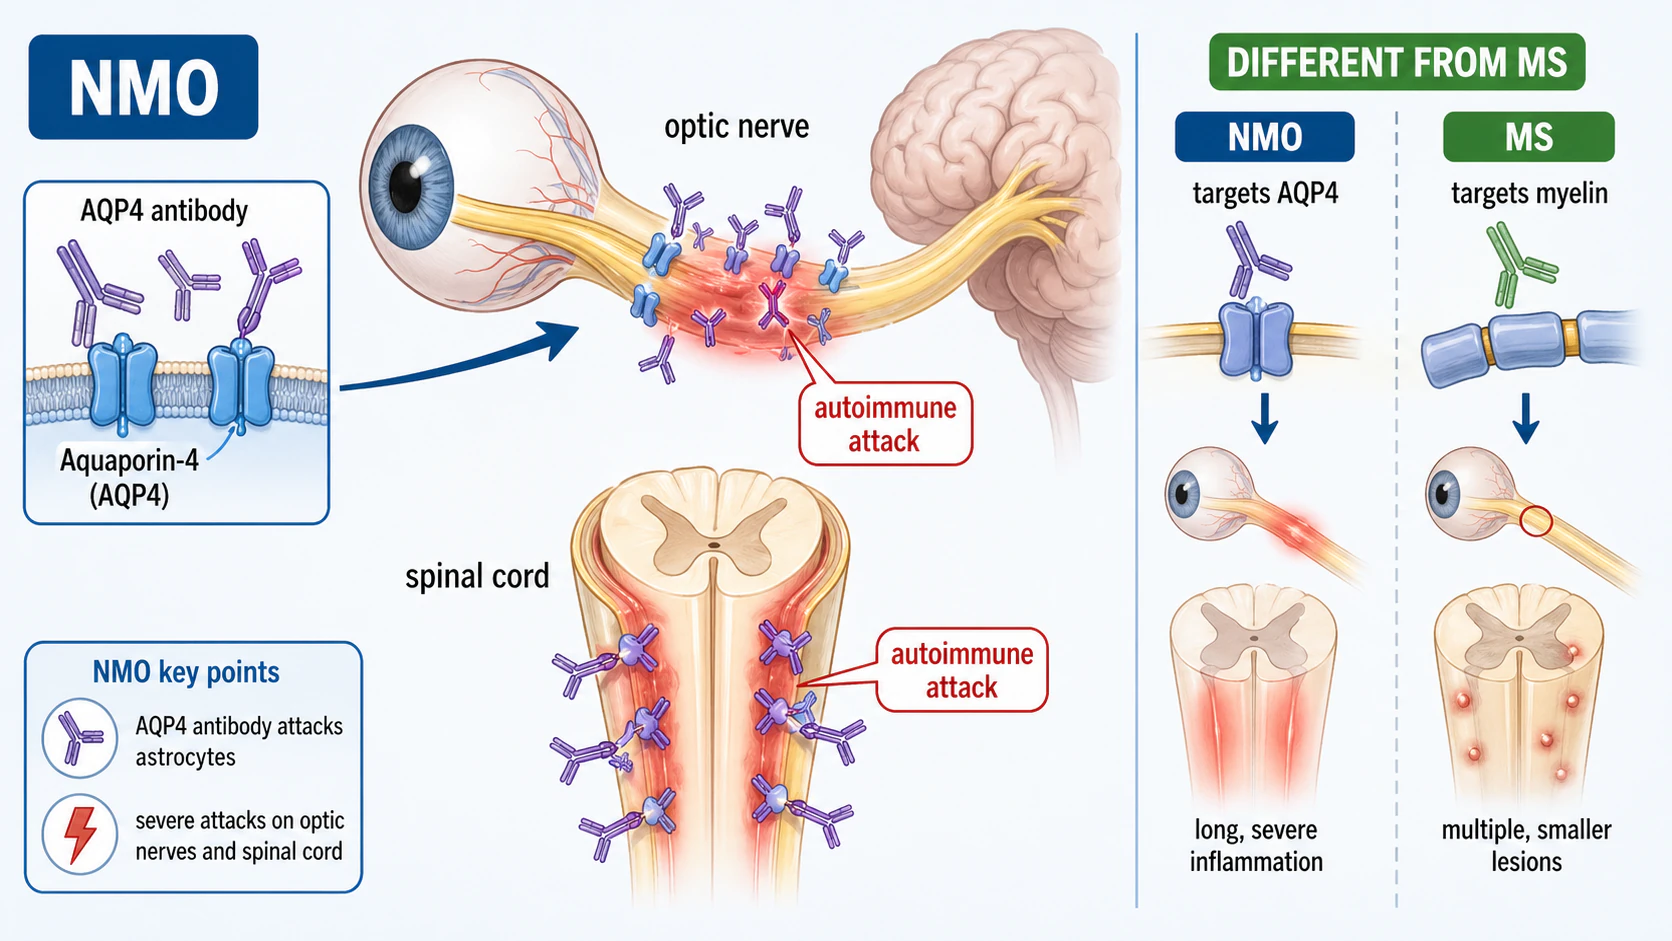
Neuromyelitis optica spectrum disorder (NMOSD), previously called Devic's disease, is a severe autoimmune condition that primarily attacks the optic nerves (causing optic neuritis) and spinal cord (causing transverse myelitis). It was once thought to be a variant of multiple sclerosis but is now recognized as a distinct disease with different antibodies and treatments.
Key takeaways
- Distinct from multiple sclerosis: different antibodies, treatment, and prognosis
- Attacks optic nerves and spinal cord preferentially
- AQP4 antibodies positive in most cases
- Attacks are often more severe than MS, with higher disability risk
- Preventive treatment is essential to reduce relapses
- MS treatments may worsen NMO; correct diagnosis is critical
Questions about your diagnosis? Contact our office
Understanding NMOSD
In NMOSD, antibodies attack a water channel protein called aquaporin-4 (AQP4), which is abundant in the optic nerves, spinal cord, and certain brain regions. This causes severe inflammation and damage.
Types of NMOSD
AQP4-positive NMOSD
- Aquaporin-4 antibodies present
- Most common form
- Classic clinical features
AQP4-negative NMOSD
- No AQP4 antibodies
- Requires stricter clinical and MRI criteria and exclusion of other causes
- Patients meeting MOGAD criteria have a separate disease, rather than an NMOSD subtype
Symptoms
Optic Neuritis
- Often more severe than MS-associated optic neuritis
- More likely bilateral or rapidly sequential
- Higher risk of poor vision recovery
- Pain with eye movement
- Severe vision loss, sometimes with visual-field defects
Transverse Myelitis (Spinal Cord Attack)
- Weakness in legs (or all four limbs)
- Sensory changes (numbness, tingling, burning)
- Bladder and bowel dysfunction
- Often "longitudinally extensive" (affecting ≥3 vertebral segments)
- May be severe with incomplete recovery
Other Features
Area postrema syndrome
- Intractable nausea, vomiting, hiccups
- May be the first symptom
- From attack on brainstem area postrema
Brain lesions
- Less common than MS
- Specific lesion patterns when present
Diagnosis
AQP4 Antibody Testing
- AQP4-IgG (NMO-IgG) blood test
- Positive in 70-80% of NMOSD
- Highly specific when positive
- Cell-based assay most sensitive
MRI Findings
Spinal cord
- Longitudinally extensive transverse myelitis (≥3 segments)
- Central cord involvement
- Optic nerve enhancement or swelling behind the eye; this MRI finding is different from visible optic disc swelling
- May involve optic chiasm
Brain
- Often normal or non-specific
- When present, pattern differs from MS
Lumbar Puncture
- CSF analysis
- May show elevated white cells and protein
- Oligoclonal bands less common than MS
Diagnostic Criteria
Diagnosis requires exclusion of a better explanation. With positive serum AQP4-IgG, at least one core clinical syndrome is required. With negative or unknown AQP4-IgG, at least two core syndromes affecting different CNS regions and additional MRI criteria are required; one must be optic neuritis, myelitis, or area postrema syndrome. A negative antibody test plus an abnormal MRI alone is insufficient.
NMOSD vs. Multiple Sclerosis
| Feature | NMOSD | MS |
|---|---|---|
| AQP4 antibodies | Positive in 70-80% | Negative |
| Attacks | Often severe | Usually milder |
| Optic neuritis | Bilateral, severe | Usually unilateral, better recovery |
| Spinal cord | Long segment | Short segment |
| Brain MRI | Often normal | Usually abnormal |
| Oligoclonal bands | 15-30% | 90%+ |
| Treatment | Different drugs | Different drugs |
This distinction matters because some MS drugs worsen NMOSD.
Treatment
Acute Attack Treatment
New or worsening vision, weakness, or bladder symptoms need same-day contact with the treating team and urgent assessment. Severe or rapidly worsening symptoms need emergency care; call 911 for sudden vision loss or stroke-like symptoms.
- A common adult regimen is IV methylprednisolone 1 gram daily for 3-5 days, followed by a specialist-directed taper
- First-line treatment
Plasmapheresis (plasma exchange)
- Started early when steroid response is insufficient; severe attacks may need plasma exchange alongside steroids
- Removes antibodies from blood
- Often very effective in NMOSD
Attack Prevention (Essential)
Relapse prevention is critical-each attack can cause permanent damage.
Relapse-prevention options:
- Eculizumab (Soliris) and ravulizumab (Ultomiris): FDA-approved C5 inhibitors for AQP4+ NMOSD; require meningococcal vaccination and infection-risk counseling
- Inebilizumab (Uplizna): FDA-approved B-cell depleting therapy for AQP4+ NMOSD
- Satralizumab (Enspryng): FDA-approved IL-6 receptor blocker for AQP4+ NMOSD
- Rituximab, azathioprine, mycophenolate, and tocilizumab: off-label or selected-use options depending on antibody status, prior relapses, comorbidities, and insurance
Avoid these MS drugs in NMOSD:
- Interferon-beta
- Natalizumab
- Fingolimod
- These may worsen NMOSD
Prognosis
Without Treatment
- High risk of severe disability
- Cumulative damage with each attack
- Significant vision and mobility loss
With Treatment
- Modern treatments have greatly improved outcomes
- Relapse rates significantly reduced
- Earlier diagnosis leads to better outcomes
- Some residual disability from attacks is common
Living with NMOSD
Preventing Relapses
- Take preventive medications as prescribed
- Regular follow-up appointments
- Report new symptoms promptly
- Vaccinations as recommended (avoid live vaccines on immunosuppression)
Managing Symptoms
- Physical therapy for mobility
- Occupational therapy for daily tasks
- Pain management
- Bladder management
- Low vision services if needed
Support Resources
- Guthy-Jackson Charitable Foundation
- National Organization for Rare Disorders (NORD)
- Online support communities
Frequently Asked Questions
Is NMOSD the same as multiple sclerosis?
No. Although they share some features (like optic neuritis), they are distinct diseases with different antibodies, different responses to treatment, and different prognosis. Our optic neuritis and MS risk guide explains how these conditions are distinguished. Correct diagnosis is critical because some MS treatments make NMOSD worse.
Will I become blind or paralyzed?
With modern treatment, many people maintain functional vision and mobility. The key is early diagnosis and effective preventive treatment. Each attack can cause permanent damage, which is why prevention is so important.
Can I stop taking medication if I feel fine?
No. Preventive treatment should continue even when you feel well. NMOSD attacks can occur without warning and cause permanent damage. Stopping treatment significantly increases relapse risk.
Is NMOSD hereditary?
NMOSD is not directly inherited, but there may be genetic susceptibility to autoimmune diseases. Having NMOSD doesn't mean your children will have it.
Can I get pregnant with NMOSD?
Pregnancy is possible but requires careful planning. Some medications may need to be stopped or changed before conception. Relapse risk may change during and after pregnancy. Work closely with your neurologist and obstetrician.
References
-
Wingerchuk DM, et al. International consensus diagnostic criteria for neuromyelitis optica spectrum disorders. Neurology. 2015;85(2):177-189.
-
Pittock SJ, Lucchinetti CF. Neuromyelitis optica and the evolving spectrum of autoimmune aquaporin-4 channelopathies. Curr Opin Neurol. 2016;29(3):318-324.
-
Guthy-Jackson Charitable Foundation. NMOSD Resources.
-
American Academy of Ophthalmology EyeWiki. Neuromyelitis Optica.
Medical Disclaimer: This information is for educational purposes only and does not replace professional medical advice, diagnosis, or treatment. If you have concerns about NMOSD or any symptoms, please consult a qualified healthcare provider.